


Orders

Profile


Wallet

Low-Lying Placenta Precautions: What Is Safe, What to Avoid, and When to Worry

 198 Likes|
 14 min
AI-Generated Summary
Quick overview in 30 seconds
- A low lying placenta occurs when the placenta attaches to the lower part of the uterus, partially or fully covering the cervix during pregnancy.
- Causes include maternal age above 35, IVF, unusual fetus position, complications in past pregnancies, multiple pregnancies, and unhealthy lifestyle habits like smoking.
- Key low lying placenta precautions include avoiding sexual intercourse, taking bed rest if prescribed, avoiding heavy lifting, eating iron-rich foods, and skipping strenuous exercise.
- What can support a healthy pregnancy with low lying placenta? Explore our Pregnancy Wellness Super Saver Combo - Stretch Marks Cream for Women 100g + Long Grain Pure Saffron for Pregnant Women (Kesar) - 2g.

 4.1
 4.5
Quick Answer
A low-lying placenta means the placenta is sitting low in the uterus, within 2 cm of the cervix. The most reassuring fact first: in about 9 out of 10 women, it resolves on its own by the later scans as the uterus grows. Until then, the main precaution is avoiding anything that could trigger bleeding, which usually means avoiding penetrative sex, heavy lifting and strenuous activity, and going straight to hospital if you bleed. Nothing you eat or do can "move" the placenta up.
Key Takeaways
Most low-lying placentas resolve by themselves. About 9 in 10 that are low at the 20-week scan are no longer low by the follow-up scan, and only about 1 in 200 women have placenta praevia at the end of pregnancy (RCOG).
You cannot cause it or prevent it. It depends on where the placenta implanted. The only modifiable risk factor is smoking. Precautions are to avoid bleeding, not to "cure" the position.
The placenta does not physically move. It ends up higher because the uterus grows around it. No food, exercise or sleeping position moves it, so ignore "how to move placenta up naturally" tips.
Precautions centre on avoiding bleeding: usually no penetrative sex, no heavy lifting or strenuous exercise, and rest as advised.
Any bleeding needs urgent medical attention, even if it is painless and stops on its own.
What Is a Low-Lying Placenta?
The placenta is the organ that develops with your baby and supplies oxygen and nutrients. Usually it attaches to the upper part of the uterus. Sometimes it attaches low down, near or over the cervix (the opening of the womb). Read more about what the placenta is and how it works.
The exact terms matter, because they are often confused:
Term | What it means |
|---|---|
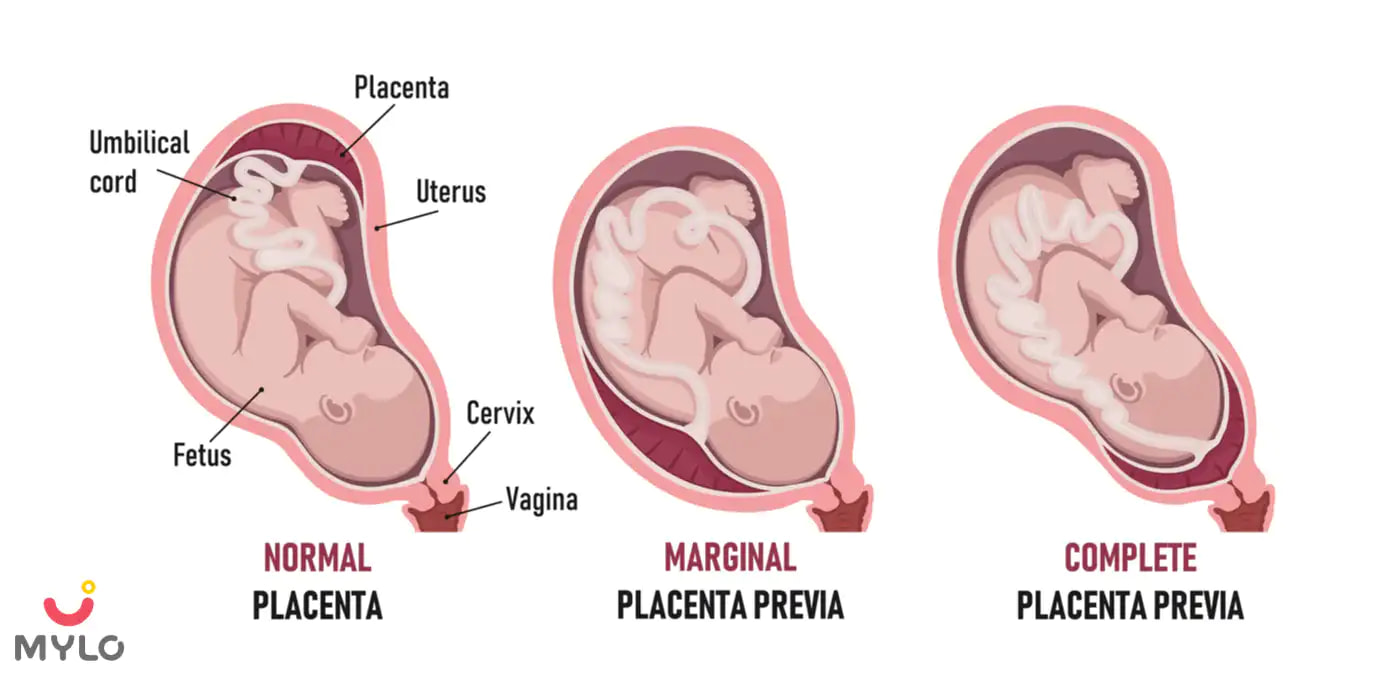
Low-lying placenta | The placenta is within 2 cm (20 mm) of the cervix but does not cover it |
Placenta praevia | The placenta completely covers the cervix |
(Definitions per RCOG.)
This distinction changes everything about the advice you get. A low-lying placenta is common at the 20-week scan and usually resolves. Placenta praevia is much rarer and more closely managed. Your scan report will tell you which one you have, and whether it is anterior (towards your front) or posterior (towards your back). Both anterior and posterior low-lying placentas are managed the same way; the front-or-back position does not change the precautions.
Will My Low-Lying Placenta Move Up? (The Most Important Thing to Know)
For most women, yes, in effect. About 9 out of 10 women who have a low-lying placenta at their 20-week scan no longer have one by the follow-up scan, and only around 1 in 200 women overall have placenta praevia by the end of pregnancy (RCOG). Research shows roughly 90% have cleared the cervix by 32 weeks and about 96% by 36 weeks.
Here is the part that stops the anxiety and the myths: the placenta itself does not move. Once it embeds in early pregnancy, it stays where it is. What happens is that the lower part of the uterus stretches and grows upward as your baby grows, carrying the placenta away from the cervix (Tommy's).
This means nothing you do can make it move. There is no exercise, yoga pose, food, knee-chest position or home remedy that moves a placenta. If you have read "how to move your placenta up naturally", it is not accurate. What you can do is attend every scan and follow your team's advice, which is exactly the plan below.
What Causes a Low-Lying Placenta, and Can I Prevent It?
You cannot prevent it, and you did not cause it. Where the placenta implants is not something you control. Certain factors make a low-lying placenta or placenta praevia more likely (RCOG; Tommy's):
A previous caesarean (and the more you have had, the higher the chance)
IVF or other fertility treatment
Having had placenta praevia before
Previous miscarriages or abortions
Smoking or drug use
Maternal age 40 or older
Twins or a multiple pregnancy
Of all of these, only smoking is something you can change, and stopping is genuinely one of the best things you can do for your pregnancy (quit smoking in pregnancy). The rest are not your fault and not preventable, so the goal is not prevention but careful management.
What Precautions Should I Take With a Low-Lying Placenta?
Every precaution below has one purpose: to avoid triggering bleeding. Follow your own doctor's advice first, as it is tailored to how low your placenta is. In general:
Precaution | Why | Practical guidance |
|---|---|---|
Avoid penetrative sex | Can cause bleeding, more so with praevia | See the dedicated section below. Ask your doctor about your situation |
Avoid heavy lifting | Strains the abdomen and pelvis | No lifting toddlers, water pots, heavy bags or gym weights |
Avoid strenuous exercise and high-impact activity | Can provoke bleeding | Gentle walking is usually fine unless told otherwise. No running, jumping or intense workouts |
Rest as advised (pelvic rest) | Reduces pressure on the cervix | Your doctor may advise "pelvic rest", meaning nothing in the vagina, including sex and douching |
Do not ignore any bleeding | Bleeding can escalate | Any bleeding means go to hospital, even if painless and light |
Avoid long or jerky travel | Distance from care, and bumpy roads | Discuss any travel or flights with your doctor first |
Attend every scan and appointment | To track the placenta's position | Do not skip the 32-week and, if needed, 36-week scans |
On bed rest: strict bed rest is not automatically recommended and has its own downsides. Whether you need to reduce activity, and how much, is a decision for your doctor based on your bleeding history and how low the placenta is. Read Mylo's guide on whether bed rest actually helps.
Can I Have Sex With a Low-Lying Placenta?
This is one of the most searched questions on this topic, so here is the honest answer.
Generally, penetrative sex is best avoided with a low-lying placenta, and it is usually advised against with placenta praevia, because it can trigger bleeding (Tommy's). How much of a risk it is depends on how low your placenta is, so this is a question for your own doctor rather than a blanket rule.
If your doctor has advised pelvic rest, that means no penetrative sex, and nothing in the vagina.
If you do have sex and notice any bleeding, stop immediately and contact your maternity unit.
Non-penetrative intimacy and closeness with your partner are a different matter and are generally not the concern here.
For general guidance, see sex during pregnancy, but for a low-lying placenta, follow your doctor's specific advice.
Best Sitting and Sleeping Positions With a Low-Lying Placenta
There is no position that moves the placenta or fixes a low-lying placenta, and no position is medically "required". That said, comfort and general pregnancy good-practice apply:
Sleeping on your side, especially the left, is the standard advice in later pregnancy for blood flow, and it applies here too.
Avoid lying flat on your back for long periods in later pregnancy.
Sit comfortably and avoid straining; there is no special "low-lying placenta sitting position" that changes the outcome.
Avoid anything that involves bearing down or heavy core straining.
If you see specific "positions to correct a low-lying placenta", treat them with caution. Position affects your comfort, not the placenta's location.
Can I Travel or Fly With a Low-Lying Placenta?
Discuss it with your doctor before booking anything. The concern with travel is twofold: bumpy or long journeys can be uncomfortable and, in a small number of cases, provoke bleeding, and travel takes you away from your maternity unit if bleeding does happen. Many women with a low-lying placenta that is being monitored are advised to stay closer to home, especially later in pregnancy or if they have had any bleeding. There is no single rule, so get personalised advice.
How Is a Low-Lying Placenta Monitored and Managed?
The plan is watchful and scan-based (RCOG):
20-week scan: the placenta's position is checked routinely.
Follow-up scan around 32 weeks: to see if it is still low. Most placentas have moved up by now. This may be a transvaginal scan, which is safe.
Further scan at 36 weeks if it is still low, to plan delivery.
If praevia persists, you may be offered steroid injections between 34 and 36 weeks to help your baby's lungs mature, because of the higher chance of early birth.
Keep every appointment. See why prenatal visits matter.
Delivery: Can I Have a Normal Delivery With a Low-Lying Placenta?
It depends on where the placenta is by the time you are due.
If the placenta has moved up (which happens for most women), a vaginal delivery is usually possible.
If placenta praevia persists, with the placenta covering or very close to the cervix, a planned caesarean is usually needed, because the placenta blocks the baby's exit and vaginal birth would risk heavy bleeding (RCOG).
Your final delivery plan is made after your late-pregnancy scan, so try not to fix your mind on one outcome before then.
When To Seek Urgent Medical Help
Go to your maternity unit or nearest emergency care immediately if you have:
Any vaginal bleeding, even if it is light, painless, or stops on its own. Bleeding from a low-lying placenta is often painless, which can be falsely reassuring
Cramping, tightening or contractions
Bleeding after sex
Reduced or changed baby movements
Any fluid loss or signs of early labour
Do not wait to see if bleeding settles. See when to make an emergency visit in pregnancy.
This article is for information only and does not replace the advice of your obstetrician, who can see your scans and tailor your precautions.
Mylo Parents Asked
"My 20-week scan says low-lying placenta. Should I panic?"
No. It is common at 20 weeks and, in about 9 out of 10 women, it resolves on its own by the follow-up scan as the uterus grows. You will be offered an extra scan around 32 weeks to check. Follow the precautions, keep your appointments, and report any bleeding, but this is usually a watch-and-wait situation, not an emergency.
"How can I move my placenta up? Are there exercises or foods?"
There are none. The placenta does not physically move, and nothing you eat, drink or do repositions it. It simply ends up higher as the lower part of your uterus stretches upward with your baby's growth. Any content promising to "move" it is not accurate.
"Can we have sex if my placenta is low lying?"
Usually it is best avoided, because penetrative sex can trigger bleeding, and with placenta praevia it is generally advised against. How strict this is depends on how low your placenta is, so ask your own doctor. If you do have sex and notice any bleeding, stop and contact your maternity unit.
"Is a posterior low-lying placenta more dangerous than anterior?"
No. Anterior means towards your front and posterior means towards your back, and both are managed the same way when low-lying. What matters is how close the placenta is to the cervix, not whether it is front or back.
"Does a low-lying placenta mean I will definitely need a C-section?"
Not usually. Because most low-lying placentas move up by the third trimester, most women go on to have a normal delivery. A caesarean is planned only if the placenta is still covering or very close to the cervix near your due date.
"Can a low-lying placenta cause miscarriage?"
A low-lying placenta found at the routine scan is not a cause of miscarriage. Its main risk is bleeding later in pregnancy, which is why the precautions and prompt reporting of any bleeding matter. If you are worried, speak to your doctor.
"I have a low-lying placenta and I have to lift my toddler. What do I do?"
Avoid heavy lifting where you can, including lifting a toddler, as it strains the abdomen. Ask family for help, sit down to cuddle your child rather than carrying them, and talk to your doctor about your specific limits. This is exactly the kind of practical issue worth raising at your appointment.
Bottom Line
A low-lying placenta sounds frightening, but for the large majority of women it resolves on its own by the later scans, and only a small minority go on to have placenta praevia. You cannot move it, prevent it or fix it with home remedies, and you did not cause it. What you can do is follow the precautions that reduce bleeding, usually avoiding penetrative sex, heavy lifting and strenuous activity, keep every scan appointment, and treat any bleeding as a reason to go to hospital straight away, even when it is painless.
References
All links verified live on 16 September 2026.
Placenta praevia, placenta accreta and vasa praevia — Royal College of Obstetricians and Gynaecologists (RCOG). Source for the definitions (low-lying vs praevia), the 9-in-10 resolution and 1-in-200 praevia figures, monitoring schedule (32 and 36-week scans), steroid injections, and delivery guidance.
Low-lying placenta and placenta praevia — Tommy's (clinically reviewed, PIF TICK certified). Source for the placenta not physically moving, prevention not being possible, anterior vs posterior, sex guidance, and risk factors.
Iron deficiency anaemia in pregnancy — internal, referenced because repeated or heavy bleeding raises anaemia risk.


Trusted by Mamas Navigating Delicate Pregnancies
Gentle, doctor-approved essentials to nourish you and your baby while you rest, recover, and follow precautions safely.
Baby Wellness Kit | Skincare Gift Set for Newborns



Compression Stocking Socks - S
Compression Stockings for Varicose Veins | Reduces Swelling | Boosts Blood Circulation


Article Posted Under
Related Articles



Related Topics

Medical Disclaimer
This content is for informational purposes only and should not replace professional medical advice. Consult with a physician or other health care professional if you have any concerns or questions about your health. If you rely on the information provided here, you do so solely at your own risk.


AWARDS AND RECOGNITION

Mylo wins Forbes D2C Disruptor award

Mylo wins The Economic Times Promising Brands 2022
AS SEEN IN













- Mylo Care: Effective and science-backed personal care and wellness solutions for a joyful you.
- Mylo Baby: Science-backed, gentle and effective personal care & hygiene range for your little one.
- Mylo Community: Trusted and empathetic community of 10mn+ parents and experts.


Product Categories
Baby Carrier | Baby Soap | Baby Wipes | Stretch Marks Cream | Baby Cream | Baby Shampoo | Baby Massage Oil | Baby Hair Oil | Stretch Marks Oil | Baby Body Wash | Baby Powder | Baby Lotion | Diaper Rash Cream | Newborn Diapers | Teether | Baby Kajal | Baby Diapers Pants | Cloth Diapers | Laundry Detergent | Lactation Granules |